

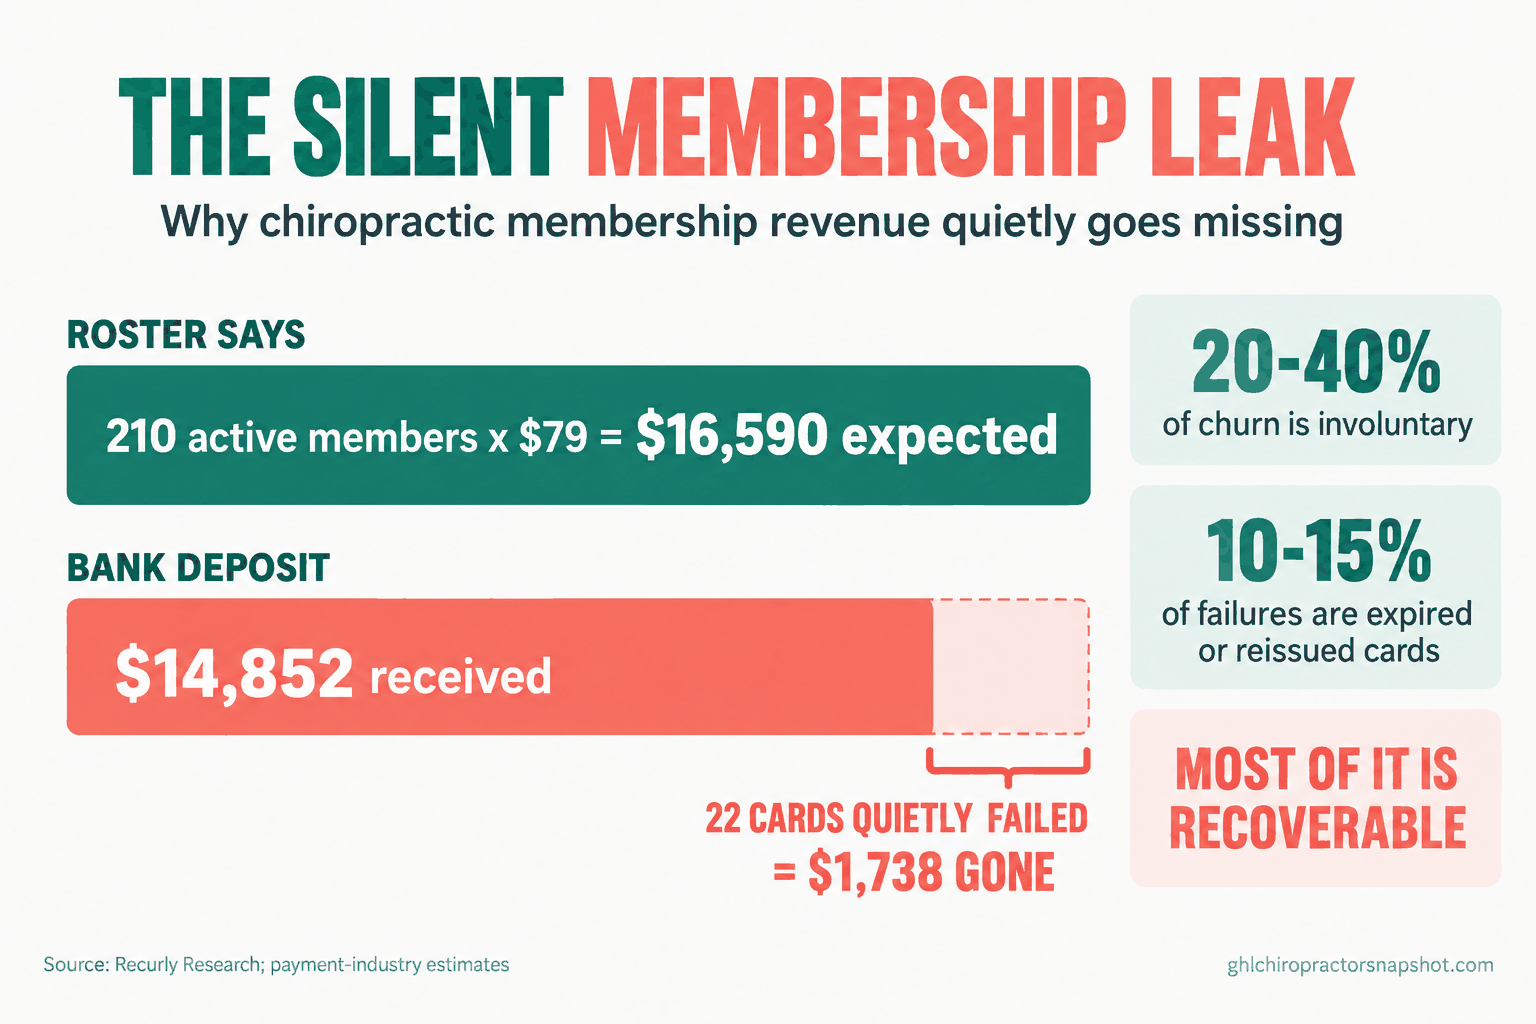
It is the last day of the month and you are reconciling the merchant statement. Your practice software says your wellness membership has 210 active patients at $79 a month, so roughly $16,590 should have landed. The deposit says $14,852. Somewhere in that gap, 22 memberships did not pay this month. Nobody cancelled. Nobody complained. The cards just quietly failed, and those patients are still walking in for care they are no longer paying for.
That gap has a name: involuntary churn, and it is the single most recoverable revenue in a chiropractic practice. A failed card is not a “no.” It is an expired Visa, a bank that flagged a recurring charge, a card reissued after a data breach. The patient still wants the care and the money is sitting there. It just needs a system to go get it, and most clinics do not have one, so the leak runs month after month and shows up only as a vague sense that membership revenue is lower than it should be.
This is the build guide for plugging that leak: how card-on-file capture should actually work, how to catch a dying card before it declines, the retry timing that recovers the most payments, the exact message sequence to send (copy you can lift), how to save the patients who really are trying to leave, and how to keep all of it HIPAA-aware and TCPA-conscious. Every outside number is sourced so you can size the leak for your own roster.
Table of contents
- The two ways a membership plan loses money
- What the leak actually costs your clinic
- The recovery system, stage by stage
- Run the numbers: solo, mid-size, multi-doc
- Staying compliant: card storage, texting, and PHI
- Objections a clinic owner actually raises
- Frequently asked questions
The two ways a membership plan loses money
A membership or care-plan subscription leaks in two very different ways, and clinics almost always fix the wrong one.
Voluntary churn is the patient who decides to leave: they feel better, money is tight, they are moving. This is the churn everyone worries about, and it is real. But it announces itself. You get the cancellation, the “I need to pause,” the reply to a reminder. You can see it, so you can respond to it.
Involuntary churn is the payment that fails while the patient is still a happy member. The card expired, the bank declined a recurring merchant, or the number changed after a reissue. The patient has no idea. Your software may quietly mark the membership past-due, or worse, keep it “active” while collecting nothing. This is the churn nobody sees, which is exactly why it is the most expensive.
Here is the part that should change how you read the month-end gap: involuntary churn is not an edge case. Across subscription businesses, failed payments make up an estimated 20% to 40% of total churn (Recurly Research), and the share runs higher in consumer-facing, card-on-file models, which is exactly what a chiropractic membership is. Payment-industry estimates put roughly 10% to 15% of those recurring failures on cards that simply expired or were reissued (Stripe). None of those patients said no. The system just never asked again the right way.
What the leak actually costs your clinic
Membership is meant to be the calm, predictable base of a practice: it smooths cash flow, funds the slow months, and rewards patients who value maintenance care. The context is big. The US chiropractic field is a roughly $24.0 billion market across about 66,061 businesses (IBISWorld, 2026), and a growing slice of those practices run wellness memberships precisely because recurring revenue beats one-off visits.
But recurring revenue only works if it recurs. When 10% of a 210-member roster silently stops paying, you are not down 21 payments once. You are down that revenue every month until you notice, plus the lifetime value of members who drift off because a failed card was never fixed. Chiropractic practices already run attrition in the mid teens, around 17% on a directional basis (ClinicMind, 2026), so a plan that also bleeds silent payment failures is leaking from two holes at once.
The good news hiding in those numbers is that involuntary churn is the rare problem where the fix is almost pure upside. You are not acquiring anyone and not discounting. You are collecting money you already earned from patients who already chose you. A layered recovery approach commonly recovers a meaningful chunk of failed payments, with typical dunning programs recovering roughly half and the best-run systems far more (Recurly). The recovery ladder makes the case on its own.
The recovery system, stage by stage
A recovery system is not one setting in your billing tool. It is six stages that hand off to each other, from the moment a card goes on file to the day a patient either pays or genuinely leaves. Build them in order.
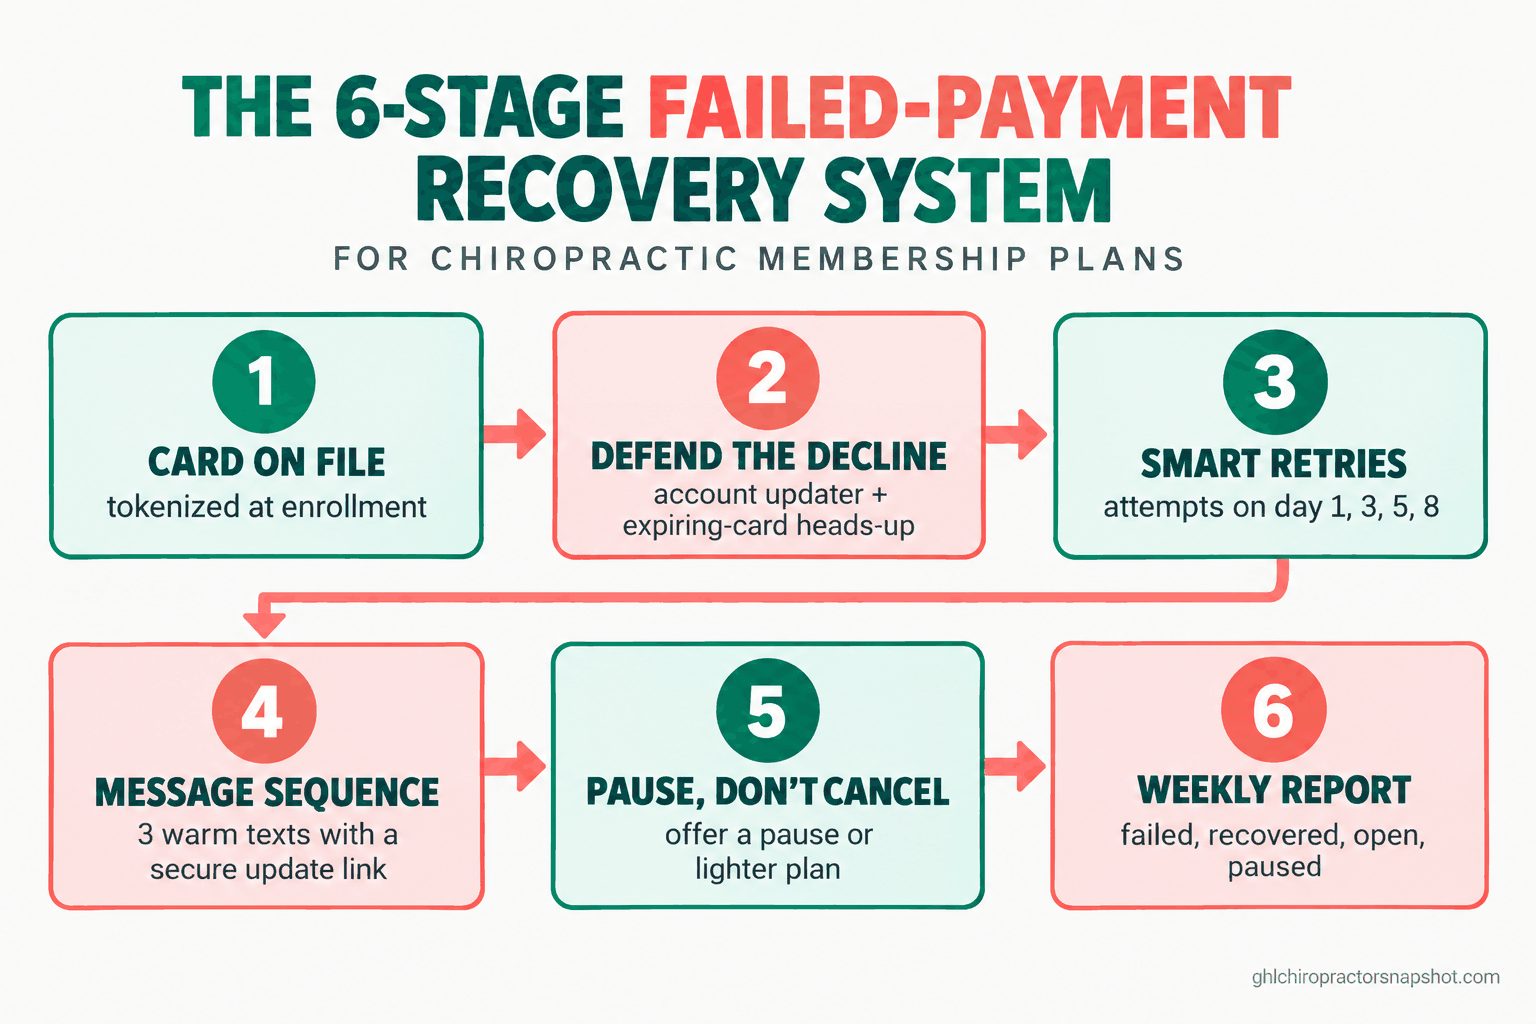
Stage 1: Capture the card on file the right way
Everything downstream depends on how the card got stored. If your front desk keys a card into a terminal each month, you have no recovery system, you have a person who forgets. The card must be tokenized and stored with your payment processor at enrollment, tied to the recurring plan, so the charge runs automatically and every later stage has something to work with.
Do it at enrollment, on a device the patient can see, with a plain sentence about what recurs and when: “This card will be charged $79 on the 1st of each month for your wellness membership. You can update or pause it anytime.” Capture the mobile number and email in the same step, with explicit consent to receive account and billing messages. Those two contact points are what make Stages 2 through 5 possible.
How it breaks: the card is stored but the contact info is stale, so a failed payment has no way to reach the patient. Or consent to text was never captured, so your only channel is a phone call the front desk never has time to make. Fix the intake once and every later stage works.
Stage 2: Defend against the decline before it happens
The cheapest failed payment is the one that never fails. Two defenses run quietly in the background.
First, a card account updater. Most major processors offer a service that pings the card networks for updated numbers and expiry dates when a card is reissued, and refreshes the token automatically. Because expired and reissued cards drive an estimated 10% to 15% of recurring failures (Stripe), turning it on eliminates a chunk of declines before any patient sees a message.
Second, expiring-card outreach. Your system knows a card expires in 08/2026 before August arrives, so send a light, friendly heads-up a few weeks out.
Hi Maria, quick housekeeping note from Lakeside Chiropractic.
The card on file for your wellness membership expires next
month. Update it here so your plan keeps running without a
hiccup: [secure link]. Takes 30 seconds. Reply STOP to opt out.
No health detail, no diagnosis, nothing but a billing note. That message alone prevents the most common and most annoying failure: a loyal patient’s card lapsing for a reason that had nothing to do with wanting to quit.
How it breaks: clinics turn on the account updater and assume it covers everything. It does not. Debit cards and smaller issuers have thinner coverage, so you still need the outreach and the retry stages behind it.
Stage 3: Retry on a schedule, not on a whim
When a charge fails, when you retry matters as much as whether you retry. Hammering the card an hour later, while the balance is still short, just burns a retry and can trip fraud flags. A smart retry schedule spaces attempts to line up with paydays and account cycles.
A workable default for a monthly membership:
- Attempt 1: the scheduled billing day.
- Attempt 2: two days later (catches a temporary hold or a just-topped-up balance).
- Attempt 3: day five.
- Attempt 4: day eight or the next likely payday window.
Between attempts, the Stage 4 message sequence runs in parallel, so the patient can fix the card before the final retry. Most billing platforms let you configure this cadence once. The goal is three or four well-timed attempts across roughly a week, not ten desperate ones in a day.
How it breaks: the default in many systems is a single retry, then a silent past-due flag. One attempt recovers a fraction of what four well-timed attempts do, and the silent flag means nobody ever tells the patient. Change the default.
Stage 4: The failed-payment message sequence (steal this)
This is the heart of recovery, and where clinics either sound like a debt collector or a helpful practice. Keep it short, warm, and about the card, never the care. Here is a three-message sequence you can lift, timed to run alongside the retries.
Message 1, same day as the first failure (SMS):
Hi James, this is Lakeside Chiropractic. Heads up: the card on
file for your membership didn't go through today. No worries,
it's usually just an expired or reissued card. Update it here
and we'll take care of the rest: [secure link]. Reply STOP to opt out.
Message 2, day three, if still unpaid (email, a little more room):
Subject: A quick fix for your Lakeside membership

Hi James, we tried your card again and it still didn't go through.
This happens a lot when a bank reissues a card. Your membership is
still active, we just need an updated card to keep it that way.

Update in 30 seconds: [secure link]
Questions? Just reply to this email or call us at (555) 123-4567.

Thanks for being part of the clinic.
Lakeside Chiropractic
Message 3, day seven, final attempt window (SMS):
Hi James, last reminder: your Lakeside membership card still
needs updating before your plan pauses. Fix it here in 30
seconds: [secure link], or call us and we'll sort it in a
minute. Reply STOP to opt out.
Notice what is not in any of them: no condition, no treatment, no diagnosis, nothing that looks like protected health information. A billing message is a billing message, the same discipline you use for HIPAA-aware patient texting everywhere else. Every message links to a secure self-service update page, so the patient fixes it at 9 p.m. from the couch instead of playing phone tag with your front desk.
How it breaks: the tone. “Your account is past due, pay immediately to avoid cancellation” makes a happy member feel like a deadbeat over a card they did not know had expired. Warm and specific recovers more than firm and cold.
Stage 5: Offer a pause before a cancel
Stages 1 through 4 recover involuntary failures. Stage 5 catches the patients who actually reply “cancel me,” and converts a hard no into a soft pause. When someone asks to cancel, or a card fails and the patient says money is tight, the worst response is to process the cancellation and move on. The better response is a small menu:
- Pause for 30 or 60 days instead of cancelling, so the relationship (and the card on file) survives.
- Downshift to a lighter plan (fewer visits, lower price) rather than dropping to zero.
- Skip one month and resume automatically.
A one-line save offer does most of the work:
Totally understand, James. Before we cancel, want us to just
pause your membership for a month instead? Your rate stays
locked and nothing charges while it's paused. Want me to set
that up?
A paused member is a future member. A cancelled member is a reactivation campaign you run later at much higher effort. The pause keeps the tokenized card and the plan intact, so restarting is one tap instead of a re-enrollment.
How it breaks: the save offer only lives in your head, so whether a patient gets it depends on which front-desk person picks up. Systematize it as the automatic reply to any cancel request, and every patient hears the pause option, not just the ones who reach your best staffer.
Stage 6: Close the loop and watch the number
The last stage keeps the other five honest: a weekly recovery report. Someone, or an automated summary, should see every week how many charges failed, how many recovered, how many are still open, and who moved to pause or cancel. Without it, you are back to discovering the leak on the month-end statement.
A single dashboard line is enough: “This week: 14 failed, 9 recovered, 3 in progress, 2 paused, 0 lost.” That row turns an invisible leak into a managed number, and it flags when an upstream stage needs attention (a spike in expired-card failures means turn on the account updater; a spike in cancels means look at your care experience, not your billing).
How it breaks: nobody owns the number. Assign it. The report is worthless if it lands in an inbox no one reads.
No recovery system vs. a real recovery system
| Plan | No recovery system | Layered recovery system recommended |
|---|---|---|
| Price | Silent leak | Recovered |
| Feature 1 | One charge attempt, then a quiet past-due flag | Smart retries across a week, timed to paydays |
| Feature 2 | Expired cards fail with no warning | Account updater fixes reissued cards silently |
| Feature 3 | Failed members keep getting care for free | Warm 3-message sequence with self-service link |
| Feature 4 | Cancels processed instantly, no save offer | Every cancel meets a pause-or-downshift offer |
| Feature 5 | Leak discovered on the month-end statement | Weekly recovery report, one owner |
| Feature 6 | Recovery depends on which staffer notices | Runs the same whoever is at the desk |
| See the automation features |
Run the numbers: solo, mid-size, multi-doc
The system pays off differently by roster size, so run it for your own shape. These are worked examples with stated assumptions, not survey data: a $79 monthly plan and a conservative 8% monthly failed-payment rate (inside the ranges above), comparing recovering nothing against recovering 70% of those failures.
Solo practice, 40 members. At 8%, roughly 3 charges fail monthly, about $237. Recover 70% and you claw back around $166 a month, roughly $1,990 a year that was silently walking out the door.
Mid-size clinic, 120 members. About 10 charges fail monthly, near $760. Recovering 70% is roughly $532 a month, about $6,380 a year, plus the retained lifetime value of members who would otherwise have drifted off.
Multi-doc practice, 300 members. Around 24 charges fail monthly, roughly $1,896. Recover 70% and that is about $1,327 a month, near $15,900 a year, before the compounding value of keeping those members on plan through the care-plan drop-off cliff.
The pattern is the honest one: the bigger your roster, the more the leak costs and the faster the system pays for itself, but even a solo practice recovers real money for zero acquisition spend. To sanity-check the upside, run it against your patient lifetime value, because a recovered member is not worth one month, they are worth the rest of the plan.
Staying compliant: card storage, texting, and PHI
A recovery system touches money and messaging, so three guardrails are non-negotiable. None are hard, they just have to be built in from the start.
Card storage is PCI, not your spreadsheet. Never store card numbers in a note, a form field, or a staff document. Cards live tokenized with a PCI-compliant processor, and your team only ever sees the last four digits. Any real billing tool handles this, but a home-grown “card on file” in a notes app is a genuine liability.
Billing texts are still TCPA texts. A payment reminder by SMS follows the same consent rules as any other automated message: capture explicit consent to receive account and billing messages at enrollment, put a clear opt-out on every SMS, honor opt-outs instantly, and respect quiet hours. The same TCPA-conscious discipline you use for appointment reminders applies to dunning messages.
Keep PHI out of the money messages. A billing message says the card failed and how to fix it. It never names why the patient comes in, their plan of care, or anything clinical. That is the HIPAA line, and it is easy to hold once your templates are written the right way.
Objections a clinic owner actually raises
“My practice software already charges the card, isn’t that enough?” Charging the card is Stage 1: it attempts the payment. It usually does not retry on a smart schedule, message the patient warmly across a week, run an account updater, or offer a pause. The gap between “attempts a charge” and “recovers a failure” is exactly the 20% to 40% of churn that is involuntary. A charge is not a recovery system.
“Won’t chasing payments annoy my loyal patients?” It annoys them far more to have their card silently lapse, lose their locked-in rate, and find out months later. Done right, a recovery message feels like a favor: “heads up, your card expired, here’s a 30-second fix.” The annoyance comes from cold, collector-style language, which is why Stage 4 is written warm.
“I only have 40 members, is this worth setting up?” The worked example says a solo practice recovers roughly $1,990 a year for no acquisition cost, and the system runs itself once built. At 40 members every one matters, and losing three a month to silent failures is a real dent in the base you are trying to grow.
“Isn’t recovery just my front desk’s job?” Your front desk is adjusting-hours triage, not a billing operations team. Asking them to remember which cards failed, retry on the right days, send the right message, and offer the right save is asking a busy human to be a workflow, and it gets done inconsistently on the days that are not slammed. The system runs the same whether the desk is quiet or three deep, the same reason clinics automate membership onboarding and retention math instead of running it by memory.
Frequently asked questions
What is involuntary churn in a chiropractic membership plan?
It is revenue you lose when a recurring payment fails, rather than when a patient decides to quit. The card expired, was reissued, or the bank declined the charge, and the patient still wants the care and does not know it failed. Across subscription businesses it makes up roughly 20% to 40% of all churn, and unlike voluntary churn, most of it is recoverable.
How much of a failed membership payment can actually be recovered?
It depends on how many recovery layers you run. A single charge attempt recovers very little. Adding smart retries, timed dunning messages, and a card account updater commonly recovers roughly half of failed payments, and the best-run programs recover far more. Recovery is cumulative: each layer catches failures the last one missed.
Why do so many recurring card payments fail?
The most common reason is expired or reissued cards, which payment-industry estimates put at roughly 10% to 15% of recurring failures. Others include insufficient funds, banks declining recurring merchants, and fraud flags on repeat charges. Expired-card failures are the easiest to prevent: an account updater and an expiring-card heads-up stop them before the charge runs.
Is it HIPAA-compliant to text a patient that their payment failed?
Yes, as long as the message contains no protected health information. A text saying the card on file failed with a link to a secure update page is a billing message, not a clinical one. Keep out any diagnosis, condition, treatment reason, or plan detail, capture consent to text at enrollment, and include an opt-out. This is general information, not legal advice.
Should I cancel a membership when the card keeps failing?
Not as a first move. Run the retries and the message sequence first, because most failures are fixable card issues, not decisions to leave. If the patient says money is tight, offer a pause, a skip, or a lighter plan before cancelling. A paused member keeps the card on file and restarts in one tap; a cancelled one becomes a much harder reactivation later.
How do I know if my clinic has a silent membership leak?
Compare your active membership count times the plan price against what actually deposited this month. If the deposit is meaningfully lower than the roster says it should be, the gap is almost certainly failed payments nobody chased. Then start a weekly recovery report so the number stops hiding in the month-end statement.
The leak was never the patients
Go back to that month-end statement and the 22 memberships that did not pay. Almost none of them decided to leave. A handful of cards expired, a few got reissued after a bank breach, one patient’s bank flagged the recurring charge and never told them. Left alone, all 22 become a silent $1,738 hole this month, and a bigger one next month as the failures pile up and a few of those patients quietly drift off because nobody ever fixed the card.
Run the six stages instead, capture the card right, defend the decline, retry on a schedule, message warmly, offer a pause, watch the number, and most of that 22 comes back this week, from patients who never wanted to leave. That is the whole trick with involuntary churn: it looks like lost patients, but it is really uncollected money waiting for a system to go get it. Build the system once, and your membership revenue finally matches the roster.
If you would rather not wire all of it by hand, the Chiropractor Snapshot installs the entire recovery system into your GoHighLevel account in about 24 hours, message templates, retry logic, save offers, and reporting included, for a single $997.